Saturday, November 2, 2013

If I collapse at work, here is a list of doctors that I don't want working on me.

Sadly all of us have such a list in our heads.

At the recent ASA meeting, I attended 2 separate ethics sessions which dealt with the same question.  If you know the surgeon is incompetent and the patient asks you, do you tell them?  The ethical answer is yes, however you could see how this would play out in the workplace should you actually do this.

A while ago I got a phone call from an exasperated colleague complaining about one of our surgeons.  This surgeon more or less restricted his practice to certain area but when on call takes on all comers.  My colleague pointed out that this surgeon had taken way longer than other surgeons to do a case with the result that that OR was now backed up with emergencies.  I had gotten the same impression so a day or so later I ran into the Chief of Surgery in the lounge and raised the question.  I obviously wasn't the first person to do so.  "His infection rate is the same as everybody else and his length of stay is the same too," spat out the Chief.  I later talked to the Chief of Staff, also a surgeon, and got the same answer.  Hmmm I thought if both of them know this surgeon's average length of stay and infection rate, maybe they had to look into it for some reason.

We had a now departed cardiac surgeon at the Centre of Excellence who was to say the least not very good.  Bad to the extent that several cardiac anaesthesiologists actually gave up doing cardiac anaesthesia rather than work with him ever again.  That's right cardiac anaesthesiologists actually gave up lucrative work because they didn't want to work with a surgeon.  (Some of them later rejoined on the condition that they not have to work with this surgeon).  One female anaesthesiologist said she felt like a murdress every time she worked with this surgeon.  One day a bunch of them were talking in our lounge about how bad this surgeon was, when I interjected, "Do you think you may be liable for working with him when you think he is incompetent?".  "That's an interesting question," replied the department chairman who had made a rare appearance to sit with the little people.  This is unlike this group of anaesthesiologists at another centre who had the cojones to refuse to work with a clearly incompetent cardiac surgeon and saved countless lives. 
The surgeon at the CofE continued to work on for a couple more years after this and is  now working somewhere in the US interestingly enough as an anaesthesiologist, as I found out on Google, which is surprising given his poor opinion of anaesthesiologists when he worked in Canada.

There are two components to surgery.  One is technical skill and one is judgement.  A surgeon may have perfect technical skills but very poor judgement and inappropriate surgery well performed can be as bad as appropriate surgery badly performed.

Incompetent surgeons come can be divided into groups.

Some surgeons are just plain incompetent.

Other surgeons learn early on that they cannot handle difficult cases and restrict their practice to a small menu of cases that they know they can do.  That is assuming there are any cases that they are able to do.   This works out especially if they work with someone who can occasionally bail them out.

The most dangerous surgeon is the surgeon who doesn't know he is incompetent.  Some of these are idiots who just blissfully ignore their bad results.  Quite a few of them a sociopaths who don't care about their bad results.  I suspect a large number of these surgeons actually know they are incompetent but have invested too much time and training and are working away waiting to get found out.  There is a subgroup who do some types of surgery quite competently but will attempt more difficult surgery with terrible results.  Quite often these individuals claim to be subspecialists in the very area they lack competence in.

A lot of us will actually tolerate an incompetent surgeon if he is pleasant to work with, works reasonably fast, doesn't do a lot of cases after hours and his cases don't come back to the OR too often.  The incompetent surgeon who is a complete asshole may get caught out sooner or conversely concerns about his work may be downplayed as "you are just complaining about him because you don't like him."  Or of course if he is a complete sociopath people including anaesthesiologists may be afraid to complain.

OKAY SO WHAT ABOUT INCOMPETENT ANAESTHESIOLOGISTS.

Yes they exist.  Some are globally incompetent, some may just have trouble with certain aspects of care like epidurals for example. When I first started out there were still a large number of anaesthesiologists with little or no formal training who had been grand-fathered in and were still working even in large centres.

Surgeons  like most bad anaesthesiologists because they rarely do regional blocks, art lines or central lines, they cut corners and never cancel cases except for the bad anaesthesiologist who has enough insight into his skills and only will do ASA 1 cases.  Further bad anaesthesiologists usually don't mind working after hours and will stay late.  Some surgeons know that the anaesthesiologist isn't really that good and just try to avoid him for their sicker patients.  Bad anaesthesiologists are either really nice guys so the nurses and the surgeons put up with the badness or they are real assholes and everybody is afraid to confront them.

Years ago there was an older anaesthesiologist whose skills had slipped which culminated in a surgeon finally refusing to work with him while on call.  This was a shock to everybody.  This individual did continue to work on for a few more years but wasn't allowed to take call, an imperfect compromise.  At our hospital we had to get rid of two anaesthesiologists about 5 years ago.  They had been there for years after training in another country.   It had been suspected for years that they less than competent but the surgeons loved them because they worked fast, never canceled cases for medical reasons and loved to work after hours.  Our department chief was forced to do a prolonged chart review of all their cases before he found enough evidence to hang them which he did and they retired.  All in all less than pleasant.
 

Friday, October 4, 2013

Good thing that Hypocratic Oath.


There is a Doonsbury cartoon about 30 years ago, based on Henry Kissinger's CABG surgery.  In the cartoon the surgeon is talking with Kissinger a day or so post-op.  He notes that during the surgery he was holding the heart of somebody who had condemned thousands to death.  He said, "Then I thought of my Hypocratic Oath and sewed you up".  Kissinger replies, "Good oath that".

A couple of months ago while working I went out to see a patient for a procedure.  His name seemed familiar so I thought that he might have been a patient I had seen before or even somebody I might have have met socially.  I asked him that and he said he didn't remember meeting me.

It was only after I put him to sleep that I realized the man who had placed his life in my hands was the insurance assessor I wrote about here.

I told the staff in the room about him and what he had put me through but at the end of the case I took him to the recovery room and went on with my business (I even gave him something for nausea) and presumably a day or so later he went on with his business and I hope to god we never meet one another again.

Open Letter to Your Friendly Emergency Room Doctor

I found this on Facebook.

Emergency room doctors certainly write a lot of blogs and rants, and they do have the most interesting stories which is is probably why they have TV shows about the ER and not about anaesthesia.

I have seen variations on this rant before either from ER doctors and nurses. I thought it was pretty fun but then I thought about the patients I see in the pain clinic and how I used to treat chronic pain patients when I worked in the ER and how chronic pain patients get treated now. Therefore.

OPEN LETTER TO YOUR FRIENDLY EMERGENCY ROOM DOCTOR.

I worked a lot of emergency shifts before I became an anaesthesiologist, both as a family doctor, and as an "emergency room physician", so I actually have some empathy for what you face and I agree with about 90% of what you say. However as a chronic pain doctor who follow chronic pain patients and writes prescriptions for oral opioids, I have to make the following points.

There are a lot of slime balls out there who like to try to fool unsuspecting doctors but there are also a lot of legitimate patients who suffer from either acute or chronic pain. The problem is the tendency to lump all these patients into a single group.

When my patients ask about going to the emergency room, I tell them that the emergency room is for people with fractures and heart attacks and that their chronic back pain is not an emergency. I try to give them some treatments and get them some skills to avoid visiting the emergency. And for the most part the patients I follow don't visit the emergency. I know this know because all emergency records are posted on our province's EMR and I check this. And many of my patients who have been to the emergency describe it as the worst experience of their lives, something they would do anything to avoid. Having said this, patients with chronic pain who take opioids do break bones, or get appendicitis. This is usually a horrible experience for them because most ER docs don't give enough analgesia to normal patients let alone narcotic tolerant patients.

Many of the problems I see in the pain clinic are the result of bad treatment in the ER. Take the episodic migraine patient who has been transformed into a chronic daily headache patient by all the injections of various narcotics, sedatives and anti-inflammatories that ER docs like to give because we all know every ER doc is an expert on treating headaches. Did it occur to you that maybe some of these patients weren't just drug seeking and were actually looking for some type of long term solution. All yeah, ER docs don't do follow up; that's what you like about ER.

Given all the bad side effects and long term consequences of NSAIDs (which all ER docs know about because they were in the top 25% of their class), is it surprising that patients maybe don't want to take them? Especially when they may have been popping OTC NSAIDs all day before they decided to go into the ER. And what is the fascination among ER docs with ketorolac (Toradol)? While it was marketed aggressively by the company as an analgesic, it is an NSAID just like all the other NSAIDs except that it can be injected. Every time I see somebody with marginal renal function who has received multiple doses of ketorolac in the ER, I shudder. None of the patients I see in the pain clinic are allergic to Tylenol. In fact one of the hardest jobs I have in the pain clinic is convincing patients not to take so much Tylenol and acetaminophen containing compounds. In Canada you can buy acetaminophen 325 mg with 8 mg of codeine and that is pretty popular. (Confession: I even get some for myself if I have a really bad cold/flu). This is posted on the patient's EMR now as well and it is interesting just how much of this some patients buy.

And why wouldn't a patient ask for a drug that he know has worked in the past? When I had a dental abscess, tylenol with codeine didn't work percocet did. Guess what I'm asking for next time?

And patients do lose prescriptions and have them stolen. If you lose your BP pills, you just call the pharmacy and they will give you another batch. Because of regulations, pharmacies can't or won't refill your opioid prescription without calling your doctor. Quite a few of my chronic pain patients lose their prescription or have it stolen. This only ever happens once. Likewise occasionally when patients run our of medication, they find that their family doctor is on holidays, has retired, or the office tells them that the next available appointment is in 2 weeks. Sure patients should plan to get their prescriptions filled when their doctor is available. Think though how often you have thru lack of planning forgot to do something really important?

And I confess to being confused by the term drug seeking. Given that about 95% of all non-surgical visits end in a prescription, aren't all patients drug seeking. I have never heard anybody talking about Ventolin seeking or nitrate seeking or Amoxil seeking patients.

Which reminds me. I used to work in the ER and see the patients like the ones described in the rant. They were a pain in the butt, but they did pay the bills if you are on fee for service. Its a hell of lot easier to order Demerol and Gravol, or whatever your migraine cocktail is, than it is to actually figure out a sick patient. And, unless things have changed since I was an ER doctor, about half the doctors just order that to the regulars without even seeing them. Of course when I covered a ER without on-site coverage it was a pain to come in from home which is why most of us just left standing orders for the 10 or so ER regulars every small town had. I can however see why you are upset about having to treat these patients. You are of course very busy with other duties in the ER (which judging from the wrecks who come up to OR from the ER doesn't include working up or resuscitating surgical patients).

When I worked in the emergency room, it wasn't the "drug seeking" patients who bugged me. I actually enjoyed the mental chess games they played with me. What bugged me were the non-compliant patients with chronic diseases who showed up with their suitcases packed asking to be admitted, the patients who came with URTIs and of course the doctors who sent their patients to the emergency room expecting you to work them up and arrange the admission. Not to mention being yelled at by specialists when I wanted a consult.

And who gives a shzt that apparently all emergency room docs were in the top 25% of their medical school classes and are therefore harder to fool. Actually I think anybody who got into medical school is pretty smart. No that's wrong, anybody who got into medical school got good marks, did the appropriate volunteer work and was able to suppress their antisocial personality traits in their admission interviews. This is not the same as being smart. I graduated 44th in a class of 89 (not at the top of class but at the top of the bell curve) and I did okay. With much of medical school marks being passed on subjective rotation evaluations, the fact that you were in the top 25% just means that you were probably good at brown-nosing and back stabbing your fellow students to make them look less good and you look better. Those of us in the bottom 75% remember just what absolute zib-zabs most of the top 25% were.

And oh yes, 30 years ago when I started practice in Canada emergency rooms were staffed by what we called general practitioners on rotation duty plus a few full-time emergency room physicians who were either young doctors fresh out of their internship or older doctors who had given up their practices. And you know what? The care that patients got was just as good then as it is now. If anything it was little better because these individuals knew their limitations.

Just something I had to get off my chest.

Friday, September 20, 2013

My Skill Set No Longer Matches Your Needs

KevinMD continues to be a fertile site for resolving my writer's block.

This is such a great statement that describes how I feel when the Pain Clinic patient shows up asking me to write a letter to fix their disability claim, their WCB case or any of the other jobs I do in the Pain Clinic which they never taught me about in medical school.

Now a lot of the patients I see in the Pain Clinic have been really fzcked over by the system and I used to be happy to spend hours on the phone, fill in forms or write letters I know nobody will read on their behalf. I am really amazed that patients think my opinion is that influential.

I know that most of the patients I see in the Pain Clinic are never going to go back to work but I do my best to try and make them more comfortable and functional. This is difficult sometimes when you spend most of the visit discussing how the patient can maximize their income support from various sources.I have become less tolerable of this complete waste of my time. I now have a stock response to the patient who complains about his treatment at the hands of Workers Comp:

You have 3 options:

1. You can do what they tell you to do.

2. You can hire a lawyer.

3. You can forget about your WCB claim and get on with your life.

For disability insurance problems, I usually advise them to get their union involved (in the small minority who have a union), or get their employer involved (he usually paid the premiums so might be interested). For welfare problems, I advise them to see their member of the legislature (it's amazing, then again maybe not, how few people know who their MLA is). One of the better funded pain clinics in our province actually has an "Entitlement Group" where patients can learn how to navigate the system.

There is of course the patient in whom I do write a letter who brings the letter back demanding revisions or asks for another letter because the letter I sent didn't get the response they were looking for. All this doesn't necessarily make me popular, like the other blogger says, "My Skill Set No Longer Matches Your Needs".

Gold Plated Equipment

Somebody printed out this article on put it on our bulletin board, so I was able find it online.

We use a lot of advanced equipment in anaesthesia and a lot of what we use has become more complicated an expensive since I have been in practice.

On the other hand, consumer goods have become more complicated but less expensive over the same time. For example I paid $600 ($1259 in 2013 dollars) for a VCR in 1983. Assuming I could even find one, I suspect I would be paying about $50 now in 2013 dollars. I bought a Blue Ray player at Costco for $100 last year. My first desktop computer with 1 megabyte of RAM cost $4000 in 1991. My latest lap-top cost just over $400. What is most medical equipment except a big computer?

As the article points out, even allowing for a modest profit, it is possible to build a videolaryngoscope for a lot less than we currently pay for one. A couple of weeks ago while walking thru Costco, I found a flexible fibre-optic camera on sale there for about $100 complete with a videoscreen. This would be useful for plumbers but it could have all kinds on other uses, like looking for the stuff that falls behind my desk. Or as I told my wife, a home sigmoidoscope. This just shows how cheaply a fibreoptic device can be made nowadays.

I wonder how much of the healthcare costs which we are told are spiralling out of control are due to the capital costs of "medical grade" equipment that we have to buy. In a country like Canada which has for all intents and purposes no electrical manufacturing sector, this means a transfer of our tax dollars to places like South Korea and China not to mention the money that gets skimmed off by American or European middlemen we have to deal with. A country with a population of 30 million like Canada could probably produce it's own cheaper medical devices on a break even basis, paying workers good wages but that would require government intervention and even a bleeding heart liberal like me doesn't trust the government that much. Bulk purchasing has been shown to work although getting multiple hospitals and practitioners to agree on one product is next to near impossible plus you give one company a monopoly and the quality of service goes down.

One of the effects of high prices is that sometimes hospitals just won't buy a piece of equipment you feel is necessary because it is too expensive. This affects surgery less than anaesthesia and a lot of the equipment we feel we "need" adds nothing to patient care; however I remember the struggle to get pulse oximeters in the mid-late 1980s. They cost $10K then despite not being much more sophisticated than a VCR and it wasn't until the price came down and (less importantly) practice standards came out that their adoption became universal.

Now of course medical equipment is a little different from consumer equipment in that it has to be sterilizable and may have higher standards of electrical safety but certainly not enough to justify the huge mark-up which as the article points out is only equalled by crack cocaine. It would be great if for all that extra money went towards a more durable product but we all know how much downtime medical equipment spends being serviced and the cost of that service.

One of the plastic surgeons told me he was going to do video-assisted carpal tunnel releases in his office. Instead of the expensive monitor the company wanted him to buy, he just went to Best Buy and picked up a flat screen TV. Expensive monitors have proliferated all over the ORs and endoscopy suites which are probably no more sophisticated (maybe less sophisticated) then the brain-sucking Big Screen TV in my mancave but probably cost 10X as much.

Consumer health products do not seem to affected by the mark-ups that the hospitals pay. You can buy a home ECG monitor like this, or a finger pulse oximeter for under $100. Devices with cables that work with your i-phone are now available.

This remains one of the real scandals in medicine and it would be nice if our politicians and media stopped harping on how much doctors and nurses get paid and looked into this.

Friday, August 30, 2013

Non-therapeutic touch


This post is puts it more eloquently than I ever could and to our credit (and to everybody elses discredit) is written by an anaesthesiologist.

Right on.  During the touchy-feelie parts of medical school I had to endure, they  talked about the importance of touching patients and how to do it in an appropriate fashion.  Aside from the touchy-feelie aspects, we learned in our physical exam sessions that you could actually get useful information like skin temperature, clamminess, edema and texture just by touching patients.  I haven't come across it yet but I suspect some people are now donning gloves just examine patients or take their blood pressure.

Nobody likes to be a vector for infection but our infectious disease department expects you to wash your hands before AND after wearing gloves so the gloves are mainly for your aesthetic protection. I wear them now for starting IVs and doing injections in the Pain Clinic but I know they don't protect against needle-sticks.

Patients in isolation are another matter and the odd time I have to assess a patient either as chronic pain consults or for anaesthetic purposes, I feel like my hands are metaphorically tied behind my back.  Trying to assess and counsel a patient while dressed up in a yellow gown, paper hat, mask and gloves sends the wrong type of message to the patient at what may be a stressful time for him plus it makes the examiner so uncomfortable that I at least just want to get things finished and get out of there as quickly as I can.  Hardly good medicine.

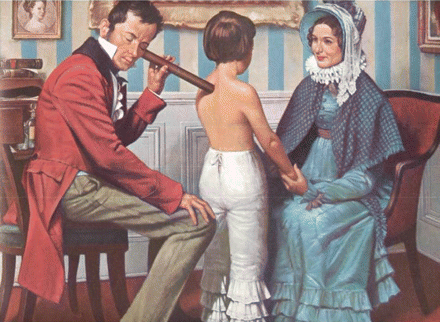
As the author points out there is a great deal of information that can be obtained with a good stethoscope and I must admit that in the holding area, I am often remiss in this.  Stethoscopes according to our infection control department are difficult to sterilize without damaging the plastic.  They haven't gone as far a banning stethoscopes which would really look bad, not that more than half of doctors even own one now, but are just ignoring this.
Laennec's stethoscope here is easily sterilized.  Maybe we should go to this one.

Thursday, August 29, 2013

Crying wolf

Something embarrassing happened to me a few years ago.  I was on call and went up on the wards to see a few patients with epidurals.  Our hospital like just about every hospital I have ever worked at periodically has the fire alarms ringing endlessly either as drill or because of what is almost always a false alarm somewhere else in the hospital.  I have no argument with hospital fire alarms going off indiscriminately.  After spending about 15 minutes on the wards listening to the alarms I retreated to the relative quiet of the operating room and went to our department's office which is adjacent to the recovery room.   I sat by the computer and started wasting time on the internet when the nurses in recovery room pushed the panic button which sends a loud alarm which can be heard all over the OR telling any anaesthesiologist who is available to get his ass to the recovery room because something bad is happening.  That would normally have been somebody like me who was sitting at the computer about 10 feet away.  Problem was having just come from an environment of alarms, I had been completely habituated and continued to surf and it was only the stampede of about 7 colleagues who had abandoned their patients on the table which alerted me that something was actually wrong.  Seeing my colleagues had the situation in hand, I slunk out of the office lest anybody ask why I hadn't gotten off my ass.

I found this  neat article on kevinmd (which despite having such a stupid name has some good stuff)

I still remember the first time I went into an operating room in second year medicine.  The one thing I remember was the sepulchral quietness of the room, the sound of the ventilator bellows, the beep of the EKG monitor, the Muzak in the background and the hushed voices.  If you went into any operating room today, it is a pretty good chance that at least one alarm will be going off.

I suspect that if most anaesthesiologists are like me, they spend a few minutes a day turning off as many alarms as their machine and monitors will allow.  Because they are annoying and they distract you from the alarms and sounds you actually need to hear.  (Actually one of my colleagues sets the alarm limits so that the alarms will go off all the time when he is working afterhours because they keep him awake.)

In 1986 when I started my residency there were very few monitors or alarms.  We had an EKG, a manual blood pressure cuff and some people used a precordial or esophageal stethoscope.  When we got the pulse oximeters many surgeons complained about the extra beep.  (The ENT surgeons of course hated them because they showed how much patients desaturated during endoscopies).  Now we have NIBPs which will alarm if the pressure is too low or high or more frequently because they can't get a reading, EKG with their alarms for high and low rates (the new monitors we bought had QT interval alarms which given that anaesthetics increase the QT, alarmed continuously until we figured out how to turn them off), ETCO2 and who knows what else.

Alarms on machines have proliferated.  The first machines I used as a resident had disconnect alarms and oxygen monitors which alarmed if the FiO2 dropped below a limit.  These were actually after-market devices which where added onto the basic machine which was sold with no alarms at all except for the ingenious fail-safe whistle which went on if the oxygen supply failed.

It was early in my residency that our local Centre of Excellence purchased it's first Drager machine not affectionately known as Herman.  Herman had alarms for everything and gave an annoying de-da-de-da-dot over and over again.  The Drager rep proudly told me that they had done research and had ascertained that this combination was the most annoying and difficult to annoy combination of sounds.  Thanks guys.   We are currently trialling machines at our hospital.  I asked the rep if it was possible to customize alarms like cell phone ring tones.  I suggested that I would like "Another One Bites the Dust".  He laughed a little nervously.

Now every anaesthetic machine comes with an array of alarms for a variety of conditions.  Some of them I don't even understand.  There are alarms like High Inspired Gas which goes off when you are trying to do a mask induction and low MAC which goes off when you are trying to wake a patient up or doing TIVA with a little gas for your own piece of mind.  When I get the alarm, I first look at the sat, the ETCO2 trace see if the patient seems to be getting anaesthetics and oxygen and then randomly make adjustments until the alarm turns itself off.  To turn off or adjust the limits on many of these alarms it is necessary to hunt through multiple menus until you get to where you are at.  This just distracts you from important things you could be doing like reading the paper, surfing the internet and oh yes monitoring the patient.

On top of this we have other alarms besides ours going off in the OR like the tourniquet which alarms after an OR plus on top of that we have the artificial noise from the cautery.  The electrical beds our hospital recently bought emit a piercing alarm when the bed is unlocked (i.e. when you are moving a patient in or out of the OR on his bed).

We started doing endoscopy sedations about 2 years ago.  After a few weeks, the supervisor came to me and asked if I could get my staff to either a)  turn the alarms off or b) do something about them.  The major culprit was the ETCO2 alarm attached to the nasal prongs.  As I found out a few months ago when I tried using it, no matter how you set the limits it basically continuously alarms even in conscious patients whom you haven't even touched yet.  Despite this our national association has made this a standard of care.  I suspect the wise people who make these standards are academic anaesthesiologists who haven't given a real anaesthetic without a bevy of techs and residents to hold their hand and wipe their bum in years.  Some people have advocated that the people we currently monitor on the ward with pulse oximeters should get these ETCO2 monitors instead.  I can only imagine the frustration of the nurses at the false alarms generated by these machines and speculate at how long before one gets pitched thru the window.

And of course it is when the shit is actually hitting the fan that the alarms become most annoying.  Like, yes I know the BP is 40/0 and I am trying to do something about it so shut the fuck up!  Our recovery room nurses are forbidden to turn off or silence alarms so the odd time I bring a patient out with sats in the 80s I have to listen to the alarm until oxygen is applied and the sat comes up on its own as it mostly always does.

It would be nice if we could say that most of the alarms actually enhance patient safety.  Anaesthesia is a lot safer now than when I started in 1986 and not because we have more alarms but because we have the pulse oximeter.  And further it is not the cut-off point of the alarm which is important.  A gradual drop in the SaO2 from 99 to 94 probably needs to be looked at and if you are going to wait for the alarm to go off at 90 you may have missed the boat.  Curiously most of our pulse oximeters have a default setting of no volume on the pleth so I have to actually turn this feature on every time. Likewise a gradual trend upwards in the heart rate may indicate something sinister well before the high heart rate alarm goes off.

I am certainly not advocating returning to the state of monitoring which existed when I started my residency. I remember as an intern working with the Professor of Anaesthesia who lectured me over the whole day on how much monitoring was unnecessary and how  he hardly ever put EKG electrodes on his patients (he even knew how much each one cost).  It would of course be interesting to know how much we spend on EKG electrodes per event recognized and treated and I suspect it is thousands of dollars, not that I am going to give up my EKG.